
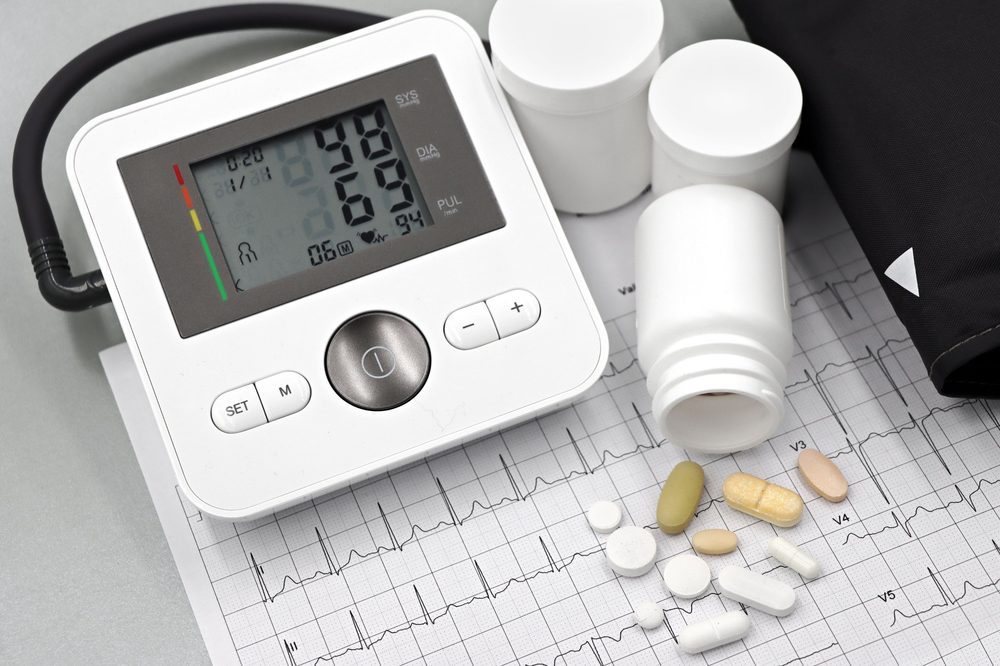
Hypertension
Regular blood pressure checks and taking medication every day help prevent stroke, heart attack and kidney damage.
Community-based NCD care in Malawi
Mlumikizi improves adherence to medication and lifestyle changes for people living with hypertension, diabetes and heart failure. It links weekly home visits by Health Surveillance Assistants with AI-assisted insights and clinical oversight.
80%
of Malawi's population lives in rural areas, where access to specialist healthcare is limited but the need for it is substantial.
Many facilities rely on diploma-level clinicians, so specialist support matters most when managing complex, chronic conditions.
At a family medicine training centre in Mangochi, poor adherence to medication and lifestyle changes stands out among patients with non-communicable diseases.
These conditions need consistent treatment, regular follow-up and lasting lifestyle change. Keeping that going between clinic visits is hard.
Mlumikizi supports people living with three of the most common non-communicable diseases, where everyday adherence makes the biggest difference.
Regular blood pressure checks and taking medication every day help prevent stroke, heart attack and kidney damage.

Daily treatment, salt and fluid guidance, and spotting worsening symptoms early keep patients out of hospital.

Consistent treatment, glucose monitoring and lifestyle support reduce the risk of long-term complications.
Mlumikizi connects community health workers, clinicians and specialist care around each patient.
 01
Health Surveillance Assistants (HSAs) visit patients every week, check how well they are following their medication and lifestyle plans, and record essential health information.
 02
Mlumikizi analyses the data collected, summarises each patient's progress, identifies potential risks and suggests tailored education and treatment-support options.
 03
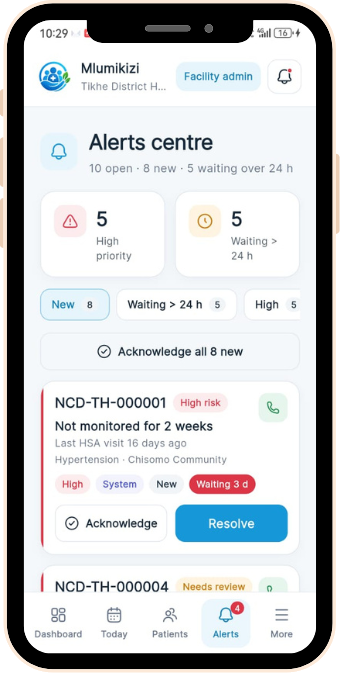
When a patient needs urgent attention, the responsible clinician is alerted so an appointment can be arranged quickly.
Reminders and priorities. The system sends reminders for scheduled visits and highlights patients who may need extra attention, so teams can focus their time and resources where they matter most.
A phone app for weekly community follow-up.
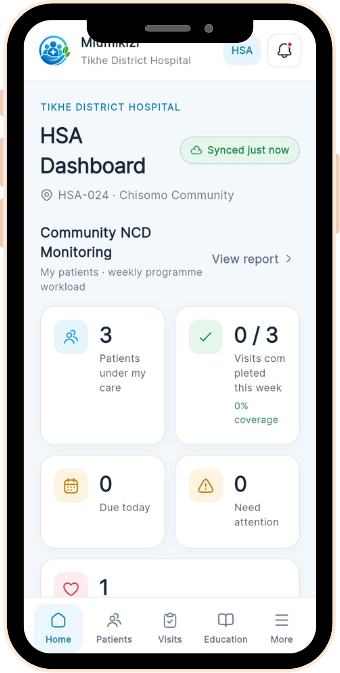
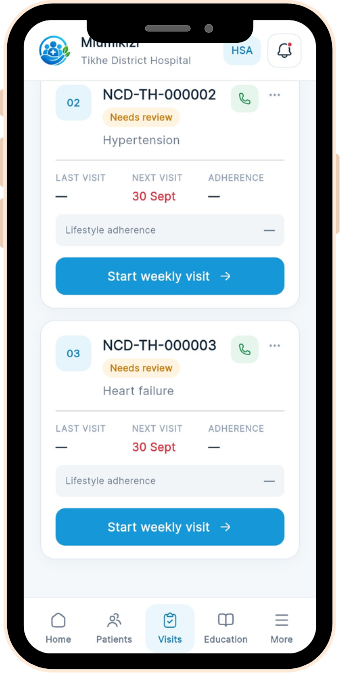
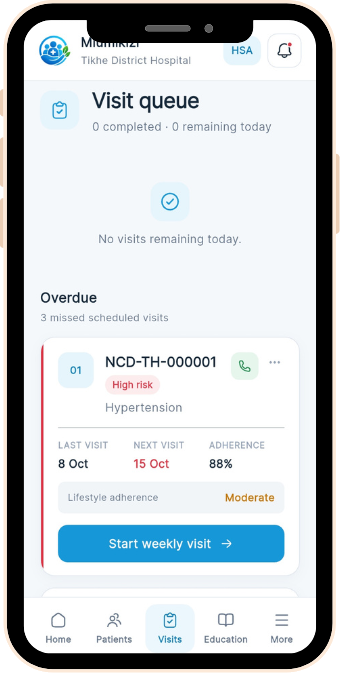
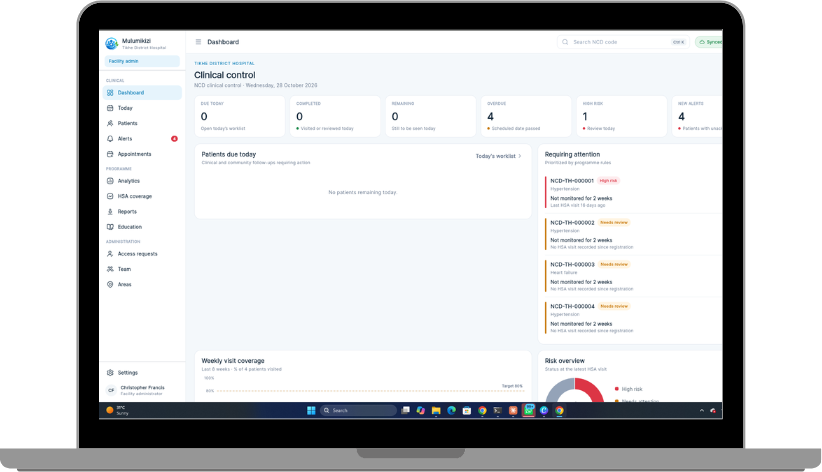
A dashboard for clinical oversight across the whole programme.
Weekly HSA visits keep patients connected to care at home.
Progress summaries and risk flags from every visit.
Clinicians see who needs attention and act early.
We are working with community health teams and clinicians to improve chronic disease care. If you would like to partner, pilot or learn more, we would love to hear from you.
